peripheral artery disease medical procedure
PAD procedures: What leg symptoms and tests can—and can’t—tell you
Can leg symptoms tell you whether a PAD procedure is appropriate?
Leg symptoms can lead to a PAD evaluation, but they cannot by themselves establish whether angioplasty or stenting is appropriate for you. The next useful step is to understand what your symptoms and test results show, then ask a clinician how those findings relate to the procedure being discussed.
A symptom is a reason to discuss evaluation; it is not, on its own, a treatment decision.
This distinction matters if you are looking up a peripheral artery disease medical procedure because you want to understand what might help your leg. The procedure name alone does not explain why it might be considered in your case. Your discussion can focus on what supports a PAD diagnosis, what the tests clarify, and what the clinician proposes next.
Before that conversation, note what you have noticed and what you want help understanding. You might be asking whether your symptoms fit PAD, what a test result means, or why angioplasty or stenting has come up. Those are related questions, but they are not answered by the same piece of information. Separating them can help you follow the reasoning without assuming that a symptom or test result settles the treatment question.
Why can PAD symptoms vary?
PAD symptoms vary, so a familiar pain pattern—or no leg symptoms—doesn’t settle whether you have PAD or need a procedure. PAD involves plaque buildup in the arteries that supply your legs, reducing blood flow; it also indicates broader cardiovascular risk.
An American Academy of Family Physicians (AAFP) article calls intermittent claudication the hallmark of atherosclerotic lower-extremity PAD, but says only about 10% of people with PAD experience it. The same article says 50% of people with PAD have a variety of leg symptoms different from classic claudication, while 40% have no leg symptoms at all. Each figure describes what occurs in groups of people with PAD; none is a personal diagnosis or a way to decide whether a procedure fits you.
That range is a reason not to rely on one familiar description of leg pain. Don’t use the absence of classic pain to rule out PAD, or a particular pain pattern to conclude that you need an intervention. Tell your clinician what you notice, including where the discomfort is, when it happens, and whether you have a wound that is not healing. Those details give you a starting point for asking what the evaluation should clarify.
You can also mention a personal or family history of heart disease or related conditions. We include those, along with leg pain when walking and non-healing wounds, among the reasons to see a cardiologist. A symptom list can help open the conversation, but the point is to discuss your situation, not to match yourself to a population statistic.

What can an ABI test add to an evaluation?
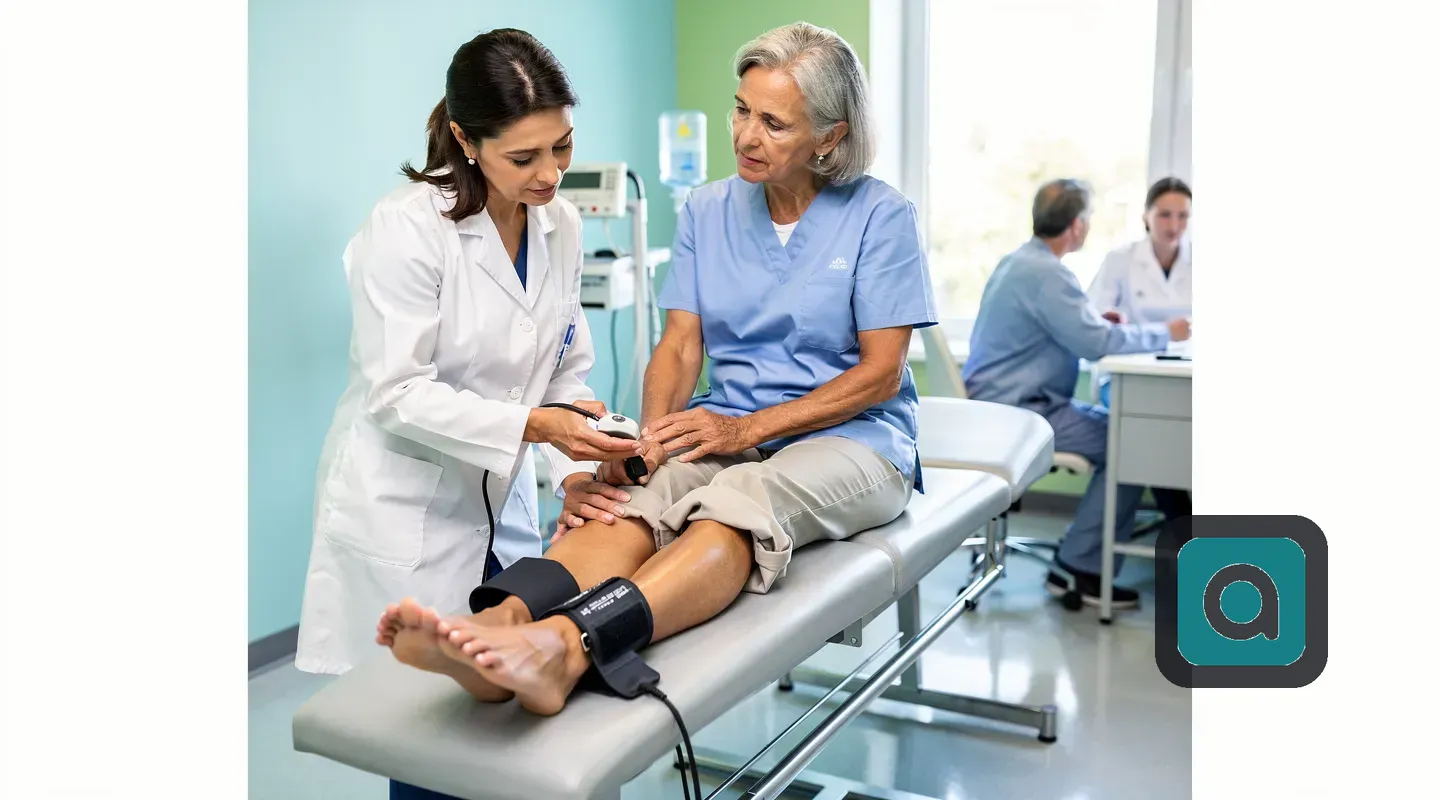
An ankle-brachial index (ABI) test can add information when your history or examination suggests PAD, but a test result alone doesn’t decide whether angioplasty or stenting fits. It is one part of an evaluation, not a stand-alone procedure decision.
The AAFP article says guidelines recommend resting ABI testing when a person’s history or examination findings suggest PAD. It also says that if you have PAD symptoms but a normal resting ABI result, exercise ABI testing can be used for further evaluation. Ask what your own result means and whether another assessment could help clarify the symptoms you described.
At Amavita Heart and Vascular Health, most patients receive non-invasive in-office testing, such as ABI, Doppler ultrasound, or vein-reflux studies, during the same visit when needed. Which tests are needed depends on the evaluation. If testing is discussed, ask what each test is intended to clarify and how the result connects with the next part of the discussion.
You can make the conversation more specific by asking what finding led to the test, what the result says about the concern being evaluated, and whether the result leaves a question to follow up. That is a question to raise with your clinician, not a conclusion to draw from the test name alone.
Keep two questions separate: what information does the test provide, and what does the clinician recommend doing with that information? Asking both can help you understand how the evaluation relates to a possible procedure without treating a single result as the whole decision.
What does the evidence establish about angioplasty and stenting?
Findings about PAD devices can inform a discussion, but a general finding doesn’t determine a personal treatment plan.
A systematic review published July 24, 2018, describes drug-coated balloons as delivering an antiproliferative agent to the artery wall. The review says this inhibits excessive smooth muscle cell growth and intimal hyperplasia, preventing vessel or stent restenosis. It presents this as a theoretical explanation and says it may explain better clinical outcomes observed compared with standard balloon angioplasty. Those qualifications matter: a proposed mechanism and a comparison between groups do not predict what will happen in your case.
The same review says covered stents may be associated with improved outcomes compared with uncovered stents in infra-inguinal interventions. “May be associated” describes a qualified comparison, not a guarantee for an individual or a rule that one device should be used in every situation.
These device comparisons provide context about particular technologies, but they do not establish which option fits an individual. A clinician discussing a possible procedure can explain those details for your situation. Which artery and findings does it relate to, and why is that option being discussed? If a drug-coated balloon or a covered stent is mentioned, ask why that device is part of the plan and what the comparison means for your circumstances.
You do not need to interpret a device finding as a recommendation. Ask for the connection between the finding, your evaluation, and the proposed approach to be explained in plain language. That keeps a general comparison in its proper place: useful context for a conversation, not a personal prediction.
What other PAD care can you discuss with a clinician?
PAD care conversations can include lifestyle measures and medicines as well as a possible procedure. The AAFP article lists smoking cessation and supervised exercise therapy among lifestyle measures for PAD. It also lists antiplatelet therapy, ACE inhibitors or angiotensin receptor blockers (ARBs), and statins among secondary prevention medicines.
Ask your clinician which measures or medicines may apply to your situation and how they relate to the findings under discussion. The list names options described for PAD; it does not tell you which choice fits your health history. You can ask what each suggested measure is intended to address and how it would fit alongside any procedure being considered.
The AAFP article names high cholesterol, high blood pressure, diabetes, chronic kidney disease, and smoking among the most significant PAD risk factors. It says having three or more of these factors confers a 10-fold increase in PAD risk. That figure describes risk in a population, not your personal likelihood or the benefit you might receive from a procedure.
The article also reports that lower-extremity PAD affects 12% to 20% of Americans aged 60 and older. This estimate offers population context; it cannot tell you whether your symptoms are caused by PAD. Your own discussion can stay focused on practical questions: Which findings support PAD in my case? What care options are being considered? How does each option relate to the findings and my health history?
Looking at procedure and non-procedure care together can help you understand what is being discussed without assuming that every option fits every person. If more than one type of care comes up, ask why each is being considered and what you should weigh before deciding.
When is leg trouble an emergency?
Sudden severe leg pain with a cold, pale limb is an emergency; go to the ER immediately. Don’t wait for a routine appointment or a discussion about a planned procedure.
Acute limb ischemia is a sudden, severe drop in blood flow to a limb, typically the leg or foot, usually because a blood clot blocks an artery. Cleveland Clinic’s explanation, published July 19, 2022, says affected tissue can quickly become damaged and may soon die. It also says acute limb ischemia needs immediate treatment to save the limb and the person’s life. That symptom pattern calls for emergency care, not a callback or routine evaluation.
If sudden severe pain comes with a cold, pale limb, go to the ER immediately.
What should you ask before discussing an intervention?
A focused set of questions can help you connect your symptoms, test results, and the options under discussion. Before the visit, write down when the leg symptoms occur, where you feel them, and whether you have a wound that is not healing. Note what you most want to understand, too. A short record of your concerns can help you explain what prompted the discussion.
- What findings support PAD in my case? Ask which details from your history or examination matter and how they connect to the assessment.
- What exactly are you proposing? If angioplasty, a stent, or both are being discussed, ask what is planned for you and why. Ask what benefits and risks you should weigh, and what recovery and follow-up would involve. Keep the question about your proposed plan distinct from general descriptions of a procedure.
- Why this device or approach? If a drug-coated balloon or a covered stent comes up, ask what the finding about that device means for your specific plan. A review published July 24, 2018, described qualified findings about these devices; ask your clinician how the comparison relates to the option being discussed.
- What other PAD care should I discuss? Ask whether smoking cessation, supervised exercise, or medicines such as antiplatelet therapy, an ACE inhibitor or ARB, or a statin are relevant to your care. The AAFP article lists these measures and medicines for PAD; ask which, if any, fit your situation.
- What is the goal of the plan? Explain what you hope to address, such as leg pain when walking or a non-healing wound, and ask how the proposed approach relates to that concern. – Which symptoms need emergency attention? Ask what should prompt urgent care rather than routine follow-up.
You don’t need to leave the conversation with a procedure decision already made. Ask for each finding and option to be explained in plain language, then make sure you understand what the clinician recommends and why. If an answer is unclear, ask the clinician to restate it in terms of your symptoms, test results, and the plan being considered.

Take your symptoms and questions to a clinician
A clinician discussion can connect your symptoms and test results with the options being considered. If sudden severe leg pain comes with a cold, pale limb, go to the ER immediately.
Bring the questions that matter most to you into that conversation. Understanding what supports the evaluation and what the proposed plan is meant to address can help you take part in the decision.
What practical questions come up about PAD evaluation?
Should people without PAD risk factors get an ABI screening test?
The AAFP article says routine ankle-brachial index (ABI) screening isn’t recommended for people who aren’t at increased risk of PAD. If you have symptoms or other concerns, ask a clinician whether testing is appropriate for your situation.
What risk factors should I mention during a PAD evaluation?
Mention high cholesterol, high blood pressure, diabetes, chronic kidney disease, or smoking if any apply to you. The AAFP article identifies these as significant PAD risk factors; having several is not, by itself, a diagnosis or a decision about a procedure.
Does PAD care include options besides a procedure?
Yes. The AAFP article lists smoking cessation, supervised exercise therapy, and certain medicines among PAD care options. Ask your clinician which, if any, fit your health history and how they relate to the findings being discussed.
Have questions about your heart or circulation?
Reading only goes so far. Leave your number and a care coordinator will call you back within one business day, or call us now.